A 3-month-old infant presented with:
Poor feeding, requiring to be fed every 2 hours and taking only 100 mls at a time rather than her usual 160mls every 4 hours.
On examination:
- Saturations 100% on RA
- Loud murmur loudest at the left sternal border
- No hepatomegaly
- No oedema
- Normal BP
The differential diagnosis included:
- Sepsis
- Congestive cardiac failure
- Congenital heart disease
A focused cardiac ultrasound demonstrated:
- A defect within the interventricular septum
- Colour Doppler showing high-velocity left-to-right flow across the septum
- Mild enlargement of the left atrium and left ventricle, consistent with volume overload
- Preserved ventricular systolic function
- No pericardial effusion
The diagnosis was a ventricular septal defect with significant left-to-right shunting.
PLAX with and without Doppler
Look carefully at the interventricular septum.
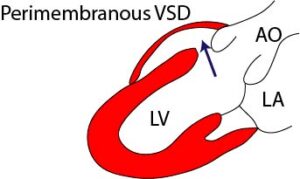
A perimembranous VSD is often seen immediately beneath the aortic valve.
Small defects may be difficult to appreciate on grayscale imaging alone.


Colour Doppler
Colour Doppler is the key investigation.
Typical findings include:
- Turbulent mosaic colour jet crossing the septum
- Left-to-right shunting
- High-velocity aliasing
Remember:
A small restrictive VSD often produces a spectacular colour jet despite causing little haemodynamic compromise.
Conversely,
A large VSD may demonstrate lower velocity flow because pressures between the ventricles become similar.
Subcostal view
VSD closed and VSD open

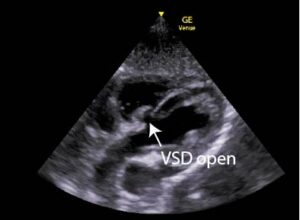
Subcostal view with colour Doppler


Why Does a VSD Cause Heart Failure?
After birth, pulmonary vascular resistance falls rapidly.
As pulmonary artery pressure decreases, blood preferentially flows from the high-pressure left ventricle into the lower-pressure right ventricle, producing a left-to-right shunt.
The consequences include:
- Increased pulmonary blood flow
- Increased pulmonary venous return
- Left atrial enlargement
- Left ventricular volume overload
- Congestive cardiac failure
This explains why infants with larger VSDs often become symptomatic at 4–8 weeks of age, rather than immediately after birth.
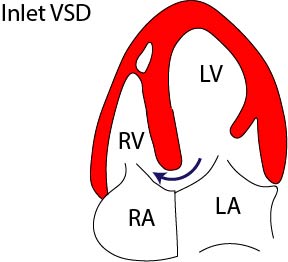
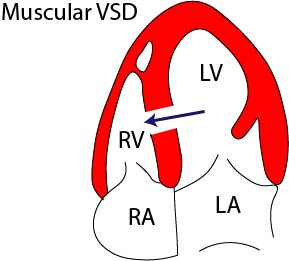
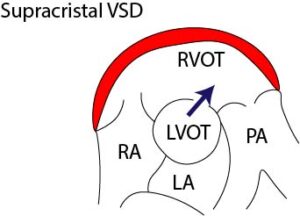
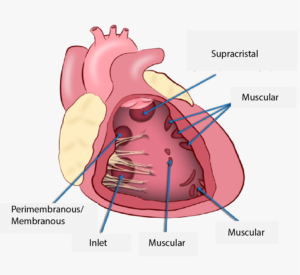
Types of VSD
The four major anatomical types are:
Type Frequency
- Perimembranous ~80%
- Muscular 5–20%
- Inlet 5–8%
- Outlet (supracristal/subarterial) 5–7%
POCUS Pearls
When scanning an infant with unexplained respiratory distress or poor feeding:
✅ Always examine the interventricular septum in multiple views.
✅ Use colour Doppler generously.
✅ Assess for left-sided chamber enlargement.
✅ Look for associated congenital abnormalities.
✅ Remember that normal ventricular systolic function does not exclude significant congenital heart disease.
Management
Management depends on the size of the defect and its haemodynamic significance.
Small muscular VSDs frequently close spontaneously and may require only follow-up.
Large defects causing heart failure are initially treated with:
- Diuretics
- Nutritional support
- Optimisation of heart failure therapy
Definitive closure is recommended when there is persistent volume overload, poor growth or pulmonary hypertension. Closure may be surgical or, in selected cases, transcatheter.
Learning Points
- VSD is the most common congenital heart defect.
- Symptoms often appear several weeks after birth as pulmonary vascular resistance falls.
- Poor feeding, tachypnoea and failure to thrive should prompt consideration of congenital heart disease.
- Colour Doppler is essential for identifying intracardiac shunts.
- POCUS can rapidly identify significant congenital cardiac lesions and expedite referral for comprehensive paediatric echocardiography.
Take home message
In infants presenting with respiratory distress, feeding difficulties or poor weight gain, don’t stop after assessing ventricular function. A careful inspection of the interventricular septum with colour Doppler can reveal a clinically significant VSD and dramatically alter patient management.
References
- Stat pearls Ventricular Septal Defect Wael Dakkak; Tony I. Oliver https://www.ncbi.nlm.nih.gov/books/NBK470330/
- https://pedecho.org/library/fetal/Fet-VSD Paediatric echocardiography : VSD
- Med J Armed Forces India. 2003 Jul; 59(3): 228–233. Published online 2011 Jul 21. doi: 10.1016/S0377-1237(03)80014-X
Congestive Heart Failure in Infants and Children Mukti Sharma,* MNG Nair,+ SK Jatana,# and BN Shahi, PVSM, AVSM, VSM, PHS* - The Practice of Clinical Echocardiography; Catherine Otto 5th edition
Leave A Comment